Sorry to interrupt your Sunday but I think it useful in these final weeks before the election to give you the truth on important matters of public policy.
Today, Republican vice-presidential nominee JD Vance told NBC News that the tariffs Trump imposed during his term in office had not raised prices for Americans but had brought a significant number of jobs back to the United States.
Wrong on both counts.
In a careful analysis, researchers found the cost of Trump’s tariffs were “almost entirely borne by U.S. firms and consumers.”
That’s not surprising; tariffs function like taxes by raising the costs of imported goods. Trump’s proposal to raise tariffs on all imports as a means of raising revenue to offset a tax cut is obviously absurd.
Vance is also wrong about employment. Research clearly shows that the Trump tariffs did not bring jobs back to the United States.
Tariffs may be necessary for national security to protect critical industries such as semiconductors. But no one should be fooled into thinking they’re costless for consumers, or good for workers. The 1930 Smoot-Hawley tariff made the Great Depression far worse than it already was.
That Vance would make these claims — which have been so convincingly debunked — should cause all of us some concern. He seems as unreliable as the person who named him his running-mate.
August 26, otherwise known as Women’s Equality Day, marks the anniversary of the certification of the 19th Amendment, which granted some women the right to vote.
Yet today, women have fewer rights than they’d had in decades. To recognize this, we acknowledge Women’s Inequality Day.
Inequality impacts our health: although women pay $15 million more each year for health care than men, we spend more of our lives in poor health. Those who may experience pregnancy no longer have reproductive freedom; and when we do give birth, we (particularly women of color) face high rates of maternal mortality.
It impacts our work: we’re paid less than our male counterparts and are underrepresented in leadership roles. We also deal with workplace harassment, insufficient maternal leave, and disproportionate caretaking responsibilities that affect our ability to work.
It impacts our representation: women are severely underrepresented in politics, making up only 25% of the Senate, 29% of the House, and 31.9% of statewide elective executives.
How can we make policies that protect and serve women without more women in office? And in an age where our basic freedoms and bodily autonomy are under fire, how can we ensure our rights aren’t degraded further?
The 2024 federal election is a critical moment in the fight for our equality.
The people we elect in November will be in charge of our rights – including the right to reproductive freedom – for the next four years.
So when you cast your vote in 2024, will you vote for someone who defends those rights? Or someone who wants to take them away?
Our 2024 campaign centers around empowering women to make their voices heard at the ballot box by equipping them with essential voter information. We’re highlighting our free, bilingual one-stop-shop for nonpartisan election information, VOTE411.org.
This year’s Women’s Inequality “Day” campaign will take place from August 26-30, with unique calls to action engaging voters every day! Get involved by sharing content via our social toolkit.
“Bad Romance: Women’s Suffrage is a parody music video paying homage to Alice Paul and the generations of brave women who joined together in the fight to pass the 19th Amendment, giving women the right to vote in 1920.” Watch here.
=====
WOMEN’S PROGRESS THROUGH THE YEARS…
Prior to 1918 Doctor’s weren’t allowed to advise married patients about birth control. Prior to 1920 Women couldn’t vote in all elections until 19th Amendment was ratified. Prior to WWII Female teachers couldn’t be married. During 1950’s Domestic abuse was not considered a crime but a’family matter’. Prior to 1963 Equitable wages for the same work, regardless of race, color, religion, national origin, or sex of the workers were not promised until passage of Equal Pay Act. Prior to 1964 Discrimination on the basis of race, color, religion, national origin, or sex was not prohibited until passage ofthe Civil Rights Act. Prior to 1965 State laws could prohibit the prescription or use of contraceptives by married couples. In some states, the woman needed her husband’s permission to purchase contraceptives. Prior to 1969 Yale and Princeton didn’t accept female students. Prior to 1969 Women couldn’t work at jobs that had been for men only. Prior to 1971 Women with a law degree could be denied the right to plead a client’s case in court. Prior to 1971 Private employers could refuse to hire women with pre-school children. Prior to 1972 The Boston Marathon was an all-male event. There was no Women’s Division. Prior to 1972 The right to privacy didn’t encompass an unmarried person’s right to use contraceptives. Prior to 1972 Title IX of the Education Amendment didn’t exist. Schools that received Federal support didn’t need to provide the same programs to women as they did men.
Prior to 1973 Abortions weren’t legal in the entire U.S. until Roe v. Wade decision by Supreme Court declared the U.S. Constitution protected a woman’s right to terminate an early pregnancy. Prior to 1974 Housing discrimination on the basis of sex and credit discrimination against women existed. Prior to 1974 It was legal to force pregnant women to take maternity leave on the assumption they were incapable of working in their physical condition. Prior to 1974 Single, widowed, or divorced women had to bring a man along to open a bank account or to cosign any credit application. Married women couldn’t open a bank account without their husband’s permission. Prior to 1975 Women were excluded from serving on juries. Prior to 1976 West Point Academy didn’t admit female students. Prior to 1977 Harvard didn’t admit female students. Prior to 1978 There was no ban on discrimination against women on the basis of pregnancy, childbirth, or related medical issues. Prior to 1984 Women were not allowed to join all-male organizations (Jaycees, Kiwanis, Rotary, Lions) Prior to 1994 There were no funded services for victims of rape or domestic violence. Prior to 2013 Women in the military were banned from combat positions. Prior to 2022 Since the 1973 Supreme Court decision (Roe v. Wade), a woman’s right to terminate a pregnancy was protected by the U.S. Constitution. This decision was reverse by the current U.S. Supreme Court in 2022. Information provided by Soroptimist site. Learn more about Soroptimist’s by visiting their site here.
LEARN MORE ABOUT THE HISTORY OF WOMEN’S EQUALITY DAY
(It’s very interesting. Well-written, but there are still little gold nuggets or Easter Eggs scattered throughout. It’s worth the click. Read it on my phone last night.)
Former MMA fighter Ronda Rousey has apologized for sharing a Sandy Hook conspiracy theory 11 years ago on X, then Twitter, saying, “I’ve regretted it every day of my life since.”
The 37-year-old Californian pro wrestler shared a lengthy statement late Thursday night (early Friday EST) saying she had long wanted to apologize in the years since sharing the controversial conspiracy, and is finally coming clean.
“I apologize that this came 11 years too late, but to those affected by the Sandy Hook massacre, from the bottom of my heart and depth of my soul I am so so sorry for the hurt I caused,” she wrote. “I can’t even begin to imagine the pain you’ve endured and words cannot describe how thoroughly remorseful and ashamed I am of myself for contributing it.”
Rousey opened her apology saying “I can’t say how many times I’ve redrafted this apology over the last 11 years.” She revealed that she internally grappled over the timing of sharing an apology and feared she could “be causing even more damage by giving it.”
It all started with what she called “the single most regrettable decision of my life” — “I watched a Sandy Hook conspiracy video and reposted it on Twitter,” Rousey wrote. (snip-More)
President Trump is refusing intelligence briefings because the Deep State continues to try and sabotage him:
“They come in, they give you a briefing and then two days later they leak it and then they say you leaked it. The only way to solve that problem is not to take them.” pic.twitter.com/8UEhoE2Qsm
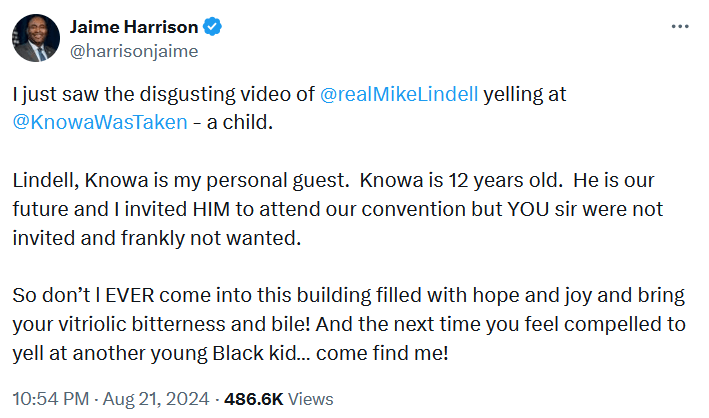
Lindell has been spotted at the United Center wandering around in a fedora to “investigate” gender-neutral bathrooms and peddle his baseless election conspiracy theories. On Wednesday, the pillowmonger got into a verbal altercation with Knowa De Brasco, a 12-year-old activist who was there supporting Kamala Harris. Read the full article. Watch all of the LOL clips.
Knowa: Lindell provided no facts, no sources. I’m confused as to why his source was ‘trust me bro’ pic.twitter.com/qXtOUbkECq
New York state lawyers urged an appeals court to uphold Donald Trump’s nearly $500 million civil fraud judgment, arguing there’s “overwhelming evidence” to support the finding that Trump lied for years about his wealth as he built his real estate empire. https://t.co/8KZh4WASDi
Read the full article. Almost all voters register using the state form. As of last month, only 42,000 Arizonans are registered to vote via the federal form.
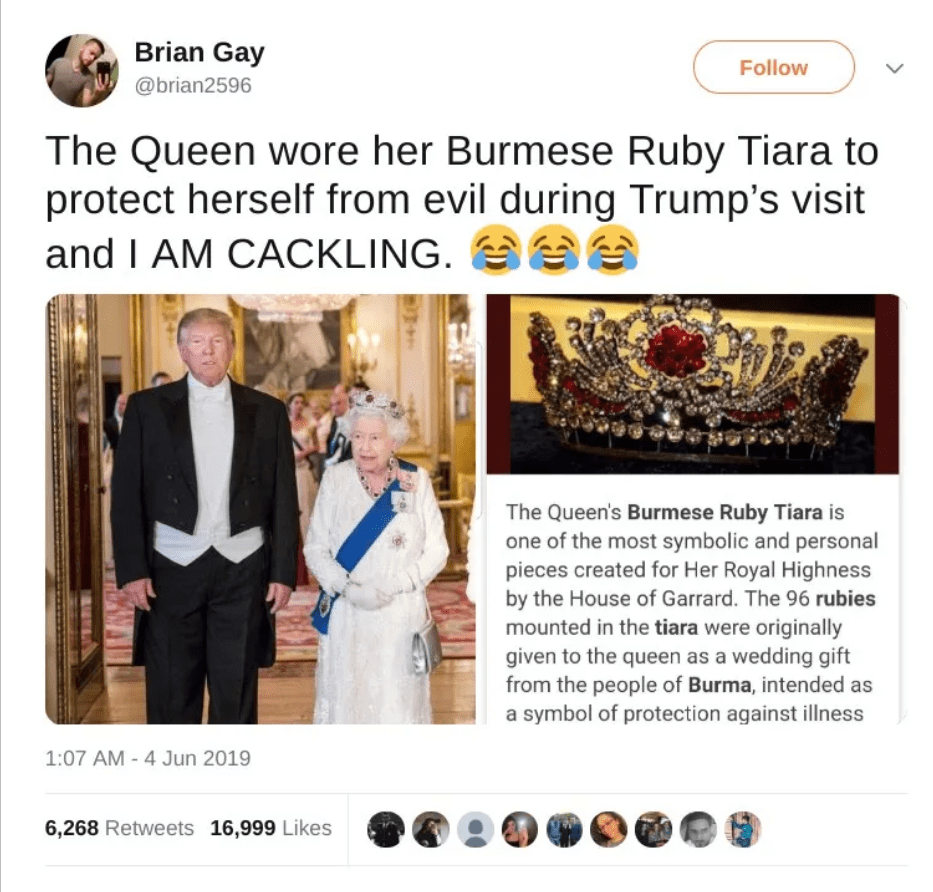
According to a coming biography, Queen Elizabeth told others that she found Trump “very rude” and that he always seemed to be looking over her shoulder “as if he was looking for someone more interesting.” The book further claims that the Queen believed that Trump and Melania must have “some kind of special arrangement,” considering his flagrant serial adultery.
Read the full article. Sentencing will be determined next week. As you can see below, Reimer’s first arrest last year resulted in a money beg from a major right wing Canadian outlet. Reimer’s previous non-drag related convictions resulted in sentences totally nearly three years.
Election officials said Arkansans for Limited Government failed to comply with state law primarily because it submitted documentation regarding paid signature gatherers separately and not in a single bundle.
As I said last month, it appears that the office of Secretary of State John Thurston [photo] deliberately withheld the above-cited rule about petition bundling. Thurston was a pastor before entering politics.
“I got a message for the Republicans and the justices of the United States Supreme Court. You can pry this wedding band from my cold, dead, gay, hand. And I’m retaining a lot of water, so good luck with that.” – Michigan AG Dana Nessel, last night.
WATCH: Michigan Attorney General Dana Nessel speaks at the Democratic National Convention.
“I got a message for the Republicans and the justices of the United States Supreme Court," Nessel said. "You can pry this wedding band from my cold, dead, gay hand.” pic.twitter.com/0rN3OuhVTt
“What they’ve done is they’ve allowed murderers, people in prisons, people in jails, people in mental institutions, insane asylums, and terrorists to pour into our country by the hundreds of thousands. And they are in our country right now, and the country that brought them out said, ‘If you ever come back, we’re giving you the death penalty or we’re gonna kill you.’” – The world’s most famous liar, inventing a death penalty for migrants who return to their home countries.
Trump claims countries are threatening migrants with the death penalty if they leave the United States and return to their country of origin. pic.twitter.com/d2kxR6czcN
“President Trump knew more about diplomacy than any president of the last 40 years. And Asia, he opened diplomatic talks with North Korea after a half century of stagnation.
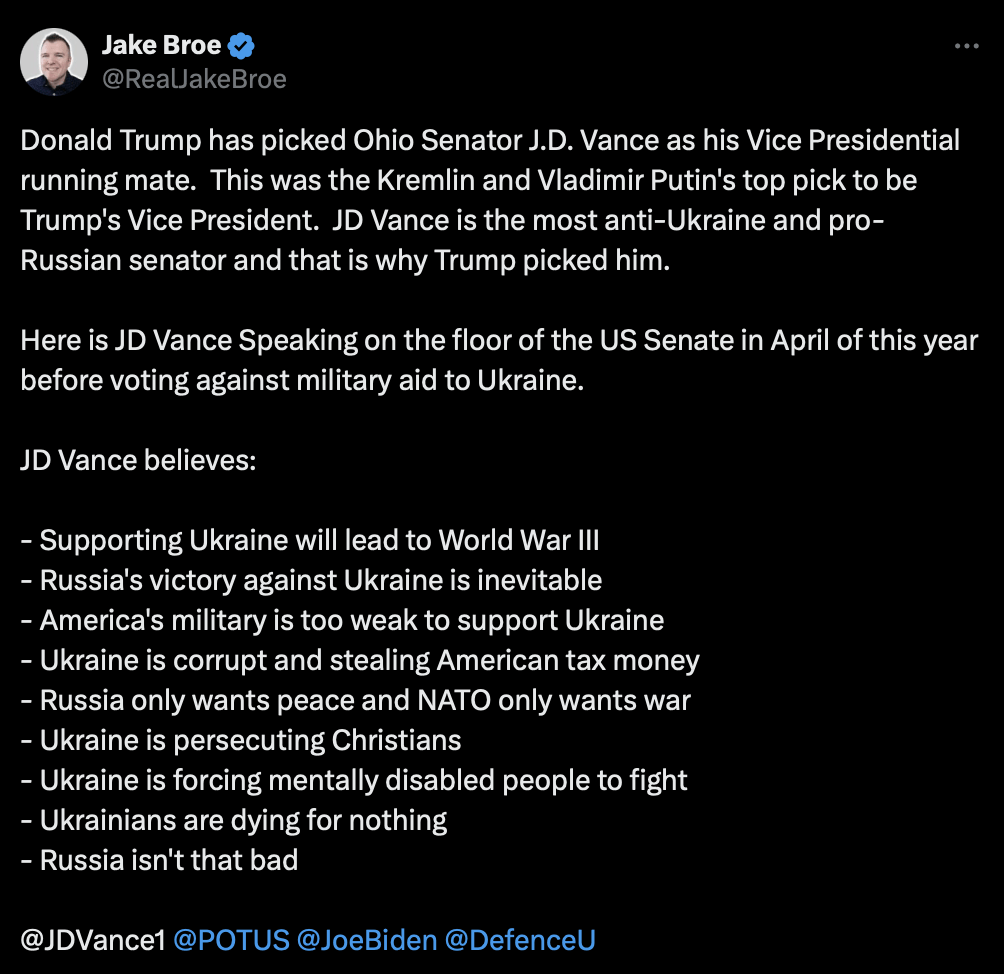
🚨 SENATOR JD VANCE: “While all these Democrats lied about Donald Trump being the candidate of nuclear war, Donald Trump is the person who prevented nuclear war, and if we're not careful, Kamala Harris is going to walk us right into nuclear war.” pic.twitter.com/juUSChErYB
LITTLE ROCK, Ark. (AP) — The Arkansas Supreme Court upheld the state’s rejection of signed petitions for an abortion rights ballot initiative on Thursday, keeping the proposal from going before voters in November.
The ruling dashed the organizers’ hopes of getting the constitutional amendment measure onto the ballot in the predominantly Republican state, where many top leaders promote their opposition to abortion.
Election officials said Arkansans for Limited Government failed to comply with state law primarily because it submitted documentation regarding paid signature gatherers separately and not in a single bundle. The group argued that it should have been given more time to provide any additional documents needed.
“We find that the Secretary correctly refused to count the signatures collected by paid canvassers because the sponsor failed to file the paid canvasser training certification” in the way the law requires, Justice Rhonda Wood wrote for the 4-3 majority.
A dissenting justice wrote that the decision strips Arkansans’ of their rights and effectively changes the state’s initiative law.
“Why are the respondent and the majority determined to keep this particular vote from the people?” wrote Justice Karen Baker, who is running against Wood for chief justice. “The majority has succeeded in its efforts to change the law in order to deprive the voters of the opportunity to vote on this issue, which is not the proper role of this court.”
The integration of artificial intelligence into public health could have revolutionary implications for the global south—if only it can get online.
(Whew! It’s a long one. Maybe read it in part, then come back and read some more. Or read it all at once, it’s not insurmountable. I’m interested what people here think about this.)
The transformative potential of digital connectivity became a global game changer more than two decades ago. Mobile phones reshaped telecommunications, enabling connectivity even in homes without landlines. Digital health quickly leveraged these innovations, making remote patient-doctor communication, digital payments, care coordination, and online peer support networks possible.
Artificial intelligence (AI) has undoubtedly sparked another phase of digital innovation. Although the field’s origins date to the mid-twentieth century, recent advancements in large language models (LLMs) have thrust it into the spotlight. Reflecting this growing relevance, the World Health Organization (WHO) dedicated a session at its World Health Assembly (WHA) in early 2024 to AI’s implications for global health, convening regional, national, academic, and international health organizations and actors to examine this matter.
AI Applications in Global Health
The literature generally presents four key use cases for artificial intelligence in health in low- and middle-income countries: disease diagnosis, risk assessment, outbreak preparation and response, and planning and policy-making. As the 2021 WHO report on AI in healthcare indicates, several AI applications are already in use or in development for diagnosis and assessment, such as in India for rapidly creating encephalograms in six minutes; in Rwanda and Pakistan for patient navigation; in Uganda, for malaria diagnosis; and in Nigeria for monitoring vital signs in mothers and children, and detecting infant asphyxia. On a broader scale, the advancement of DeepMind’s AlphaFold system in predicting the three-dimensional shape of proteins holds promise for enhancing our understanding of diseases and accelerating treatments.
Use cases in outbreak surveillance and response are also prominent. Google Flu Trends used search engine queries to predict influenza activity, but its overestimation of flu prevalence demonstrated the need for continuous algorithm updates. Tools like HealthMap have also proven valuable, detecting early signs of vaping-related lung disease and issuing an early bulletin about the novel coronavirus in Wuhan.
AI is also being used in planning and policy making, such as in South Africa where machine-learning (ML) models were used to predict how long recruited health workers’ would commit to their placements in rural communities; and in Brazil where artificial neural networks were used to create a method to geographically optimize resources based on population health needs.
Could AI Represent a Sea-Change in Global Health?
The integration of AI in public health is still evolving and being cautiously assessed in some cases, but it’s poised to transform key health functions. Evidence generation, the foundation of health policies and practices, is undergoing significant change. Traditionally, systematic reviews, a cornerstone of evidence synthesis, may take months or even years to complete. Now tools like Eppi-Reviewer use ML for more efficient screening, while platforms like Open Evidence are able to summarize existing studies rapidly. As AI becomes capable of handling technical aspects such as quality appraisal, meta-analysis, and synthesis with high rigor and fidelity, its role in evidence generation will expand. This advancement will enable more cost-effective and timely production of health guidelines, with leading bodies already creating guidelines for AI use in evidence synthesis.
Data collection and analysis are also experiencing transformative changes. AI-powered tools enable rapid analysis of both structured and unstructured data, marking a significant shift from traditional paper-based methods and conventional fieldwork. This capability has a remarkable impact on public health strategies centered on behavior change. AI can allow for the creation of highly targeted health promotion campaigns with unprecedented speed and precision. Moreover, sentiment analysis tools can assess public perceptions in real-time, enabling agile adjustments to ongoing health campaigns.
The healthcare workforce is also expected to evolve as AI-human partnerships are normalized. For instance, Hippocratic AI’s generative models can perform certain care management functions, while Google’s Med-Gemini provides real-time feedback on medical procedures, including surgeries. As they improve and are adopted by practitioners, these tools will have the potential to enhance the cost-effectiveness and precision of healthcare delivery.
As of May 2024, the FDA had authorized 882 AI- and ML-enabled medical devices. The rising volume of such AI-enabled devices as well as the rise in registered clinical trials related to their use underscores how much the field has embraced such tools.
A Changing Actor Landscape
The integration of AI in healthcare is not only transforming practices but also reshaping the landscape of global health actors. Historically, global health was a multilateral activity, dominated by international non-governmental organizations and national governments alike. The early twenty-first century saw the emergence of influential philanthropic actors like the Gates Foundation. Now, we are entering a phase where private-sector AI companies are poised to become increasingly influential in this arena.
While open-source models and government-developed AI systems exist, the predominance of private-sector AI models, such as OpenAI’s ChatGPT and Google’s Gemini, raises critical questions about data governance in global health. Unlike existing cross-national commercial influences on health such as the fast food or tobacco industries, AI systems present more nuanced concerns. For instance, if private models become integrated into existing multilateral health initiatives, how can we ensure their compliance with global health objectives? How do we address potential conflicts of interest when companies hold influence over health data and decision-making?
Regional and national guidelines are emerging to govern this evolving landscape. The European Health Data Space, discussed at the World Health Assembly, offers one such example. This initiative aims to create a single data space across the twenty-seven EU member states, empowering patients to control their health data while establishing a framework for safe data reuse and AI deployment. It also includes provisions for rigorous evaluation of high-risk AI systems in healthcare.
Similarly, the African Union recently launched its Continental AI Strategy, with a stated aim “to harness artificial intelligence to meet Africa’s development aspirations and the well-being of its people, while promoting ethical use, minimizing potential risks, and leveraging opportunities.” Monitoring measures like this as they develop will be instructive for the future deployment of AI in global health initiatives.
Building Foundational Infrastructure
Another factor to consider is that advances in AI mean little for health systems at an insufficient level of maturity. Progress in AI depends heavily on a strong foundation of digital health architecture, which encompasses secure data management, interoperability between health information systems, and comprehensive digital strategies. While most countries have digital health strategies, their implementation varies widely, with progress in resource-limited settings often lagging. Several countries have neither sufficient health workers to regularly input data nor dependable electricity and Wi-Fi to support a transition from paper to digital records. The lack of foundational infrastructure presents a significant barrier to AI implementation.
Initiatives like the Precision Public Health Initiative, led by the Rockefeller Foundation in collaboration with the WHO, UNICEF, global health funding agencies, ministries of health, and technology companies aim to strengthen AI use in low- and middle-income countries (LMICs). With initial funding of US$100 million, it aims to extend the use of AI and data science in LMICs, providing the latest technology to under-resourced parts of the world. Initiatives like this will need to concentrate resources on foundational health system strengthening functions such as the training and supportive supervision of staff and resource management.
Ethical Implications
As AI advances, ethical considerations must keep pace. These challenges can be broadly categorized into privacy and surveillance concerns, data misuse, algorithmic biases, and issues of transparency and liability. Recent cases highlight the urgency of addressing these matters proactively.
As the research report Ethics and Governance of Artificial Intelligence for Health: WHO Guidance explains, during the COVID-19 pandemic, China’s Alipay introduced a “Health Code” that used collected data to determine exposure risks. This system, which determined individuals’ mobility based on their assigned color codes, raised concerns about privacy, rights, and the potential for mass surveillance. Another case discussed in the WHO guidance report is Dinerstein vs. Google, in which the University of Chicago shared patient records stripped of identifying information with Google to develop machine-learning tools for predicting medical events. A class action complaint was filed, alleging that records could be re-identified, threatening patient privacy.
Several cases other cases in the WHO guidance report highlight the critical issue of bias in AI systems. In Argentina, an AI system designed to predict adolescent pregnancy faced criticism when it was found to have flawed methodology and to violate the privacy of adolescents. Similarly, a study in the US revealed racial biases in an algorithm that resulted in Black patients receiving less medical attention than equally sick white patients.
Additionally, an AI technology designed to detect potentially cancerous skin lesions was trained primarily on data from lighter-toned individuals in Australia, Europe, and the US, highlighting its inadequacy for darker-skinned populations.
The “black box” nature of many AI algorithms also raises critical questions about informed consent and liability. If an AI system recommends a specific drug dosage, but the underlying algorithm is opaque to the physician, who bears responsibility for adverse outcomes?
A Case Study
To illustrate how the various considerations of AI in global health converge, the WHO’s Smart AI Resource Assistant for Health (S.A.R.A.H.) project provides a recent and relevant case study. Launched in April 2024, S.A.R.A.H. is a video-based generative AI assistant designed to address gaps in health information accessibility. Developed in partnership with Soul Machines Biological AI, this initiative represents, in the words of WHO Director-General Dr. Tedros Adhanom Ghebreyesus, “how artificial intelligence could be used in future to improve access to health information in a more interactive way.”
The potential for LLMs in health promotion must be viewed against the backdrop of the burden placed on health systems. For example, Sub-Saharan Africa and South Asia have an estimated 0.2 and 0.8 doctors per 1000 people, respectively, compared to 4.3 in the European Union and 3.4 in North America. A map of travel time to health facilities reveals that it’s not uncommon to spend a day traveling to see a doctor in several regions such as North Africa. Even when they can see a doctor, more than a billion people are driven into poverty each year because of exorbitant health care costs. In such contexts, LLMs can complement the health promotion efforts currently being provided by community health workers. They can also enhance supervision and training.
S.A.R.A.H. stands out for its efforts to tailor recommendations to local contexts. For example, it offers meal recommendations based on regional dietary habits. It also uses visual emotional cues to display empathy. Like its WhatsApp-based chatbot predecessor for sharing COVID-19 information, S.A.R.A.H.’s reach will probably expand through partnerships with telecommunications providers and social networks, supporting its broad dissemination.
However, S.A.R.A.H. faces some challenges that mirror broader issues in AI for global health. Users have noticed errors in the information S.A.R.A.H. has provided; it incorrectly stated, for example, that a drug for Alzheimer’s was still in clinical trials when the drug had been approved in 2023. This highlights the critical need for AI systems to keep pace with rapidly evolving medical knowledge.
While S.A.R.A.H. offers a wider range of languages than many existing tools (including French, Russian, English, Spanish, Hindi, Portuguese, Arabic, and Chinese), this still represents only a fraction of global languages, potentially limiting its reach. Also, the success of video-based tools like S.A.R.A.H. depends on robust digital infrastructure and access to smartphones with video capabilities, which are hardly universally available.
The processing of users’ video data also raises important privacy considerations. While not yet available, the WHO has committed to making the training materials and the evidence base for S.A.R.A.H. publicly accessible, aligning with its principles on LLM use. Transparency in how S.A.R.A.H. processes and uses data will be crucial in maintaining trust and offering insights for this emerging space.
Conclusion
As noted by WHO Director-General Dr. Tedros at the WHA, AI represents a transformative advancement in global health akin to past innovations such as the introduction of vaccines, penicillin, MRI machines, and human genome mapping, all of which revolutionized the field. As reported in the above-linked 2021 WHO report on AI in healthcare, the integration of AI into health systems presents immense potential with projections noting that the top ten AI applications in health could result in an estimated US$150 billion in savings by 2026.
While the potential of AI is undeniable, the critical question remains: can it fulfill the promise of improving health outcomes worldwide? This hinges on several factors, including building foundational infrastructure, addressing ethical considerations, and effectively governing the evolving landscape of actors, which are no small feats.
August 22, 1958 President Dwight Eisenhower announced a voluntary moratorium on nuclear weapons testing. A report outlining a system for monitoring and verifying compliance of a complete ban on such testing had been released just the day before. The Conference of Experts, as it was known, had been meeting in Geneva, Switzerland, to work out the details on detection of violations of such a treaty. The U.S. delegation was led by Nobel physics laureate Ernest Lawrence from the University of California (the Lawrence Livermore National Laboratory is named after him). Eisenhower predicated his moratorium on U.S.S.R. and U.K. agreement to the same limitations. All three countries agreed to the one-year halt in testing and to begin negotiations on a complete test ban at the end of October; all three performed last-minute (atmospheric) tests before the opening of talks.
August 22, 1964 Fannie Lou Hamer, leader of the Mississippi Freedom Democratic Party (MFDP), testified in front of the Credentials Committee at the Democratic National Convention. She was challenging the all-white delegation that the segregated regular Mississippi Democrats had sent to the presidential nominating convention. Singing at a boardwalk demonstration: Hamer (with microphone), Stokely Carmichael (in hat), Eleanor Holmes Norton, Ella Baker . Mississippi’s Democratic Party excluded African Americans from participation. The MFDP, on the other hand, sought to create a racially inclusive new party, signing up 60,000 members. The hearing was televised live and many heard Hamer’s impassioned plea for inclusion of all Democrats from her state.The hearing was televised live and many heard Hamer’s impassioned plea for inclusion of all Democrats from her state. In her testimony she spoke about black Mississippians not only being denied the right to register to vote, but being harassed, beaten, shot at and arrested for trying. Concerned about the political reaction to her statement, President Lyndon Johnson suddenly called an impromptu press conference, thereby interrupting television broadcast of the hearing. Hear her testimony Link to photo gallery
August 22, 1971 The FBI (Federal Bureau of Investigation) arrested twenty in Camden, New Jersey, and five in Buffalo, New York, for conspiracy to steal and destroy draft records. Eventually known as the Camden 28, most were Roman Catholic activists, including four priests, and a Lutheran minister. “We are not here because of a crime committed in Camden but because of a war committed in Indochina….” Cookie Ridolfi The Camden 28
August 22, 1972 Rhodesia’s team was banned from competing in the Olympic Games with just four days to go before the opening ceremony in Munich, Germany. The National Olympic Committees of Africa had threatened to pull out of the games unless Rhodesia was barred from competing. Though the Rhodesian team included both whites and blacks, the government was an illegal one, controlled by whites though they represented just 5% of the country’s population. It had broken away from the British Commonwealth over demands from Commonwealth member nations that power be yielded to the majority. Read more
August 22, 1986 The Kerr-McGee Corporation agreed to pay the estate of the late Karen Silkwood $1.38 million ($2.68 in 2008), settling a 10-year-old nuclear contamination lawsuit. She had been active in the Oil, Chemical and Atomic Workers union, specifically looking into radiation exposure of workers, and spills and leaks of plutonium. The story of Karen Silkwood